Adrenal crisis
Bottom line
- Think of it early. Shock, vomiting, abdominal pain or confusion in someone with known adrenal insufficiency or long-term steroid use. In over half of patients, adrenal failure is first found during a crisis.1,2
- Hydrocortisone 100 mg IV or IM now. Don't wait for results. Draw cortisol and ACTH first only if that causes no delay.1,2
- Then fluids and a steady dose: 1 L of isotonic saline in the first hour, and hydrocortisone 200 mg over 24 hours by infusion or 50 mg every 6 hours.1,2
- Steroid users count, whatever the drug, route or dose. If they are unstable, vomiting or have diarrhea, treat as a possible crisis.3
- Crises are common and can kill. Even educated patients had 8.3 crises per 100 patient-years, with 0.5 crisis-related deaths per 100 patient-years.4 Send every patient out with sick-day rules, an injection kit and an emergency card.1,2
Who and when to suspect
- Primary adrenal insufficiency: autoimmune adrenal failure, adrenalectomy, congenital adrenal hyperplasia. Missing aldosterone adds to the risk.2
- Secondary adrenal insufficiency: pituitary or hypothalamic disease.2
- Steroid users: suppression is expected with prednisolone-equivalent doses of 5 mg or more for over 4 weeks. Long-term joint injections, skin creams and inhalers count too.2 Risk rises with more potent drugs, higher doses, longer courses, and more than one route at once.3
- Who to test: acutely ill patients with unexplained volume depletion, hypotension, hyponatremia, hyperkalemia, fever, abdominal pain or hyperpigmentation (strong recommendation).1
- Rising numbers: Swiss crisis admissions rose over 2012–2022, driven mainly by central (secondary) adrenal insufficiency and peaking in patients over 80.6
| Feature | What you see |
|---|---|
| Circulation | Hypotension, a postural drop of 20 mm Hg or more, collapse, shock.2 Shock may respond poorly to vasopressors.12 |
| Gut | Abdominal pain, tenderness or guarding, nausea, vomiting; most marked in primary disease.2 |
| Brain | Confusion or drowsiness; delirium or coma when severe.2 |
| Other | Fever, fatigue, weight loss, back and leg cramps.2 |
| Skin | Primary: darkening, especially palm creases, nipples, scars and mouth. Secondary: pale skin.2 |
| Bloods | Low sodium; high potassium (primary); raised creatinine; anemia, sometimes eosinophilia. Low glucose mostly in children.2,1 |
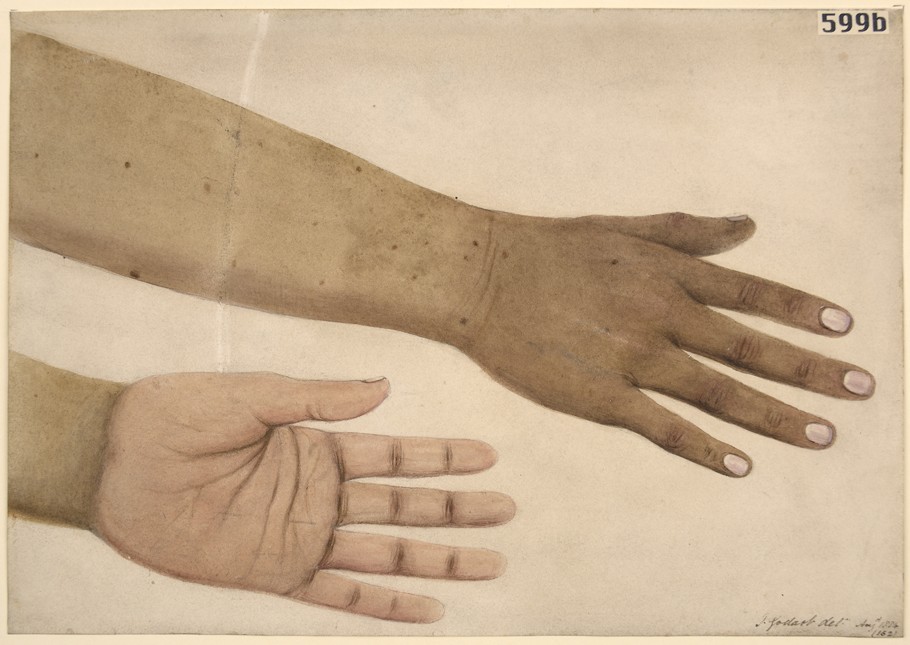
The diagnosis is often missed. In 216 patients, over two-thirds saw at least 3 doctors and 68% were first given another diagnosis, most often psychiatric or gastrointestinal.8
First hour
- Draw blood for cortisol, ACTH, electrolytes, creatinine, glucose and a blood count, but only if it causes no delay.1,2
- Give hydrocortisone 100 mg IV or IM immediately. There is no known harm in starting it, and the diagnosis can be confirmed after recovery.1,2
- Run 1 L of isotonic saline in the first hour. Further fluid is usually 4–6 L over 24 hours. Watch for overload in older patients and those with kidney impairment.2
- Continue hydrocortisone 200 mg over 24 hours by continuous infusion, or 50 mg IV or IM every 6 hours.1,2
- Find and treat the trigger. Gastrointestinal illness and other infections are the commonest.1
- Call endocrinology urgently for advice on tapering and on the cause.2
- Isotonic saline 1 L in the first hour, then more as needed, usually 4–6 L over 24 hours.2
- No hydrocortisone available?YesUse prednisolone. Dexamethasone only if nothing else is available; it has no mineralocorticoid effect.1
- Then, for everyoneGlucose low?YesGive 5% glucose in isotonic saline as the fluid. Low glucose is rare in adults.1
- Either way
Treatment
| Treatment | Adult dose | Notes |
|---|---|---|
| Glucocorticoid | ||
| Hydrocortisone (bolus) | 100 mg IV or IM, immediately | Before any test result (strong recommendation).1,2 The label lists IV and IM use and names hydrocortisone the drug of choice for adrenal insufficiency.11 |
| Hydrocortisone (maintenance) | 200 mg per 24 h by infusion, or 50 mg every 6 h | Reduce to 100 mg a day the next day; taper with endocrinology after recovery.1,2 |
| Prednisolone | If hydrocortisone is unavailable | Dose per institutional protocol and label.1 |
| Dexamethasone | Least preferred; only if nothing else | No mineralocorticoid effect.1 |
| Fluids | ||
| Isotonic saline | 1 L in the first hour, then as needed (usually 4–6 L over 24 h) | Or 5% glucose in isotonic saline. Watch for overload in older patients and kidney impairment.1,2 |
| Mineralocorticoid | ||
| Fludrocortisone | Not needed while hydrocortisone is above 50 mg a day | Primary disease: 100 µg daily once hydrocortisone falls below 50 mg a day.1,2 Not for steroid-induced adrenal insufficiency.3 |
Unreviewed doses. Verify against the current label and your institution's protocol before giving anything.
How much hydrocortisone after the bolus? The Endocrine Society and the Society for Endocrinology give 200 mg over 24 hours, or 50 mg every 6 hours.1,2 LITFL lists 100 mg IV every 6 hours.12 This page follows the guidelines.
- Subcutaneous hydrocortisone works too. In 12 patients with Addison's disease, 100 mg SC raised cortisol above 36 µg/dL in 22 minutes versus 11 minutes for IM, with similar peaks. Most patients preferred SC.9
- Fludrocortisone is rarely needed acutely. Hydrocortisone above 50 mg a day has enough mineralocorticoid effect.1,12
Patients on steroids
- Cover stress unless testing has ruled out suppression. Patients with current or recent steroid use who haven't been tested should get stress-dose cover when stressed.3
- Unstable, vomiting or diarrhea: consider adrenal crisis regardless of the steroid's type, route or dose, and give parenteral glucocorticoid and fluids.3
- Severe illness needing admission (sepsis, significant trauma, persistent vomiting): hydrocortisone 100 mg IV or IM, then 200 mg over 24 hours, or 50 mg IV every 6 hours.3
- Minor illness: patients already taking hydrocortisone 40 mg, prednisone 10 mg or dexamethasone 1 mg a day or more usually need no increase unless they are hemodynamically unstable.3
- Short courses: under 3–4 weeks, steroids can be stopped without a taper, whatever the dose.3
- The months after stopping are risky. Mortality rose sharply in the first 3–6 months after stopping long-term oral steroids.3
Testing
- Never let testing delay treatment.2 Draw paired cortisol and ACTH before the first dose if you can.1,2
- Confirm later. The ACTH (cosyntropin) stimulation test is for when the patient is stable.2 A peak cortisol under 18 µg/dL (500 nmol/L) at 30 or 60 minutes indicates adrenal insufficiency; cutoffs depend on the assay.1
- A single cortisol: a morning value under 5 µg/dL (140 nmol/L), read together with ACTH, suggests adrenal insufficiency when stimulation testing isn't possible. No evidence supports a random cortisol to rule it out.1
- Thyroid: check TSH and free T4. Don't start thyroxine for a TSH of 10 mU/L or less, because a crisis itself can raise TSH.2 Starting thyroxine can trigger a crisis.1
Triggers
- Gut illness and infection lead. In adults, gastrointestinal disease caused 32.6% of crises and other infections 24.3%.1 In a prospective study, gastrointestinal infection, fever and emotional stress each caused 20%, and 7% had no clear cause.4
- Stopping steroids abruptly, or not following sick-day rules.2
- Drugs that speed cortisol clearance, such as CYP3A4 inducers.1
- Primary adrenal failure from hemorrhage or infection, including meningococcemia.12
- Who is at higher risk: a previous crisis (OR 2.85).4 Type 1 diabetes (IRR 2.09) and both younger and older age.5 Patients with diabetes or asthma reported more crises.7
Disposition and prevention
- Admit and involve endocrinology for tapering and the cause.2
- Sick-day rule 1: double the oral dose for fever needing bed rest or antibiotics.2 The Endocrine Society doubles it above 38 °C and triples it above 39 °C, usually for 2–3 days.1
- Sick-day rule 2: injectable glucocorticoid for prolonged vomiting or diarrhea, trauma or surgery.2
- Injection kit: hydrocortisone sodium succinate 100 mg, with training for the patient and family.1,2
- Emergency card and medical alert ID for every patient.1,2
- Why it matters: only 12% of patients with a crisis injected themselves, and over two-thirds relied on medical staff for first treatment.1 Patients who adjusted their own doses more often had fewer crises.10
Pitfalls
- Waiting for a cortisol result, or a stimulation test, before giving hydrocortisone.1,2
- Ruling out adrenal insufficiency on a random cortisol.1
- Missing it in steroid users because the dose looked small or the route was inhaled, topical or a joint injection.2,3
- Reaching for dexamethasone first. It is the least preferred choice and has no mineralocorticoid effect.1
- Labelling vague fatigue and vomiting as psychiatric or gastrointestinal illness.8
- Discharging without sick-day rules, an injection kit and an emergency card.1,2
How strong is the evidence?
Immediate parenteral hydrocortisone is a strong recommendation from moderate-quality evidence, and the choice of prednisolone over dexamethasone is a weak one.1 Almost all advice for steroid-induced adrenal insufficiency is good clinical practice or rests on low or very low certainty evidence.3 Crisis rates come from cohorts: 8.3 per 100 patient-years in a German prospective study, and 3.2 overt crises per 100 person-years in a 24-year Norwegian registry, where 0.3% of admissions ended in a crisis-related death.4,5 For an emergency medicine review, see Lentz and colleagues.13
On-shift teaching
Questions to ask a learner at the bedside. Tap a question to see the answer. Every answer uses facts cited above.
Q1A hypotensive patient may be in adrenal crisis. Should you wait for a cortisol level?
Q2What fluid and how much in the first hour?
Q3Why isn't fludrocortisone started in the ED?
Q4A patient uses only an inhaled steroid and is vomiting and hypotensive. Can it be adrenal crisis?
Q5Which skin sign separates primary from secondary adrenal insufficiency?
Q6How common is crisis in patients who have been taught how to prevent it?
References
What this page is built on
13 sources, cited 120 times. Dots are sources, filled by how far each was read; stronger color means a larger share of the citations. Tap a tier to see its sources.
Checked by the writer, not a physician. The dots show how each source was read, not that anyone has confirmed the claims.
- 1Bornstein SR, Allolio B, Arlt W, et al. Diagnosis and treatment of primary adrenal insufficiency: an Endocrine Society clinical practice guideline. J Clin Endocrinol Metab. 2016;101(2):364–389.
- 2Arlt W; Society for Endocrinology Clinical Committee. Society for Endocrinology endocrine emergency guidance: emergency management of acute adrenal insufficiency (adrenal crisis) in adult patients. Endocr Connect. 2016;5(5):G1–G3.
- 3Beuschlein F, Else T, Bancos I, et al. European Society of Endocrinology and Endocrine Society joint clinical guideline: diagnosis and therapy of glucocorticoid-induced adrenal insufficiency. J Clin Endocrinol Metab. 2024;109(7):1657–1683.
- 4Hahner S, Spinnler C, Fassnacht M, et al. High incidence of adrenal crisis in educated patients with chronic adrenal insufficiency: a prospective study. J Clin Endocrinol Metab. 2015;100(2):407–416.
- 5Stokland AM, Breivik L, Dalen I, et al. Risk and outcomes of adrenal crisis in primary adrenal insufficiency: evidence from a 24-year nationwide cohort study. J Intern Med. 2026;300(5):675–688.
- 6Gafner S, Leitner K, Schuetz P, et al. Incidence and hospital outcomes of acute adrenal crisis in a Swiss-wide cohort study. Eur J Endocrinol. 2026;194(4):441–453.
- 7White K, Arlt W. Adrenal crisis in treated Addison's disease: a predictable but under-managed event. Eur J Endocrinol. 2010;162(1):115–120.
- 8Bleicken B, Hahner S, Ventz M, Quinkler M. Delayed diagnosis of adrenal insufficiency is common: a cross-sectional study in 216 patients. Am J Med Sci. 2010;339(6):525–531.
- 9Hahner S, Burger-Stritt S, Allolio B. Subcutaneous hydrocortisone administration for emergency use in adrenal insufficiency. Eur J Endocrinol. 2013;169(2):147–154.
- 10Chifu I, Burger-Stritt S, Schrader A, et al. Predisposing factors for adrenal crisis in chronic adrenal insufficiency: a case-control study. Eur J Endocrinol. 2023;189(5):537–545.
- 11Solu-Cortef (hydrocortisone sodium succinate) for injection. US prescribing information. DailyMed.
- 12Nickson C. Adrenal insufficiency. Life in the Fast Lane, Critical Care Compendium; 2022.
- 13Lentz S, Collier KC, Willis G, Long B. Diagnosis and management of adrenal insufficiency and adrenal crisis in the emergency department. J Emerg Med. 2022;63(2):212–220.
AI-generated draft. Not reviewed by a physician. This page is for education only and may contain errors, including in doses. Do not use it to diagnose, treat or make decisions about any patient. Rely on your own clinical judgment, your institution's protocols and current drug labeling. Reading this page does not create a physician-patient relationship. Full terms