Acute ischemic stroke
Bottom line
- Image fast. Get a non-contrast CT or MRI, ideally within 25 minutes of arrival. In suspected large-vessel occlusion, don't hold CT angiography for a creatinine result.1,2
- Thrombolyse disabling deficits within 4.5 hours. Use tenecteplase 0.25 mg/kg (max 25 mg) or alteplase 0.9 mg/kg (max 90 mg). The guideline endorses either.1,2,3,4
- Minor and non-disabling? Use dual antiplatelets, not a thrombolytic.1,5 In ARAMIS, dual antiplatelet therapy was noninferior to alteplase (excellent outcome 93.8% vs 91.4%).6
- Thrombectomy for large-vessel occlusion up to 24 hours in selected patients, now including large cores and basilar occlusion. If a patient is eligible for both, give the thrombolytic, then go straight to thrombectomy without delay.7,2,5
- After reperfusion, don't push systolic BP below 140. Aggressive lowering brings no benefit after thrombolysis and causes harm after thrombectomy. Don't aim for tight glucose control either.2
Recognition and triage
- Use a validated prehospital stroke scale and pre-notify the receiving hospital (both Class 1).1,2
- Mobile stroke units (ambulances with a CT scanner) are recommended where available for thrombolysis-eligible patients (Class 1, level A).1,2 In BEST-MSU, median onset-to-treatment was 72 vs 108 minutes, and 55.0% vs 44.4% of eligible patients reached a modified Rankin score of 0–1.8
- Where the nearest hospital can't do thrombectomy, the guideline focuses on shortening door-in-door-out times at the transferring hospital.7
The AHA release says EMS should take suspected large-vessel occlusion to the nearest thrombectomy-capable center.7 But where local stroke centers give thrombolysis well and transfer efficiently, the guideline finds no 3-month benefit from bypassing them for a more distant thrombectomy center (Class 3: no benefit).2 In RACECAT (n = 1,401, rural Catalonia), direct transport did not change 90-day disability. Patients taken directly got thrombolysis less often (47.5% vs 60.4%) and thrombectomy more often (48.8% vs 39.4%).9 Follow your regional protocol.
First 25 minutes
- Establish the time last known well. It sets every treatment window.2,5
- Judge whether the deficit is disabling, not just the NIHSS number. That decides thrombolysis.5
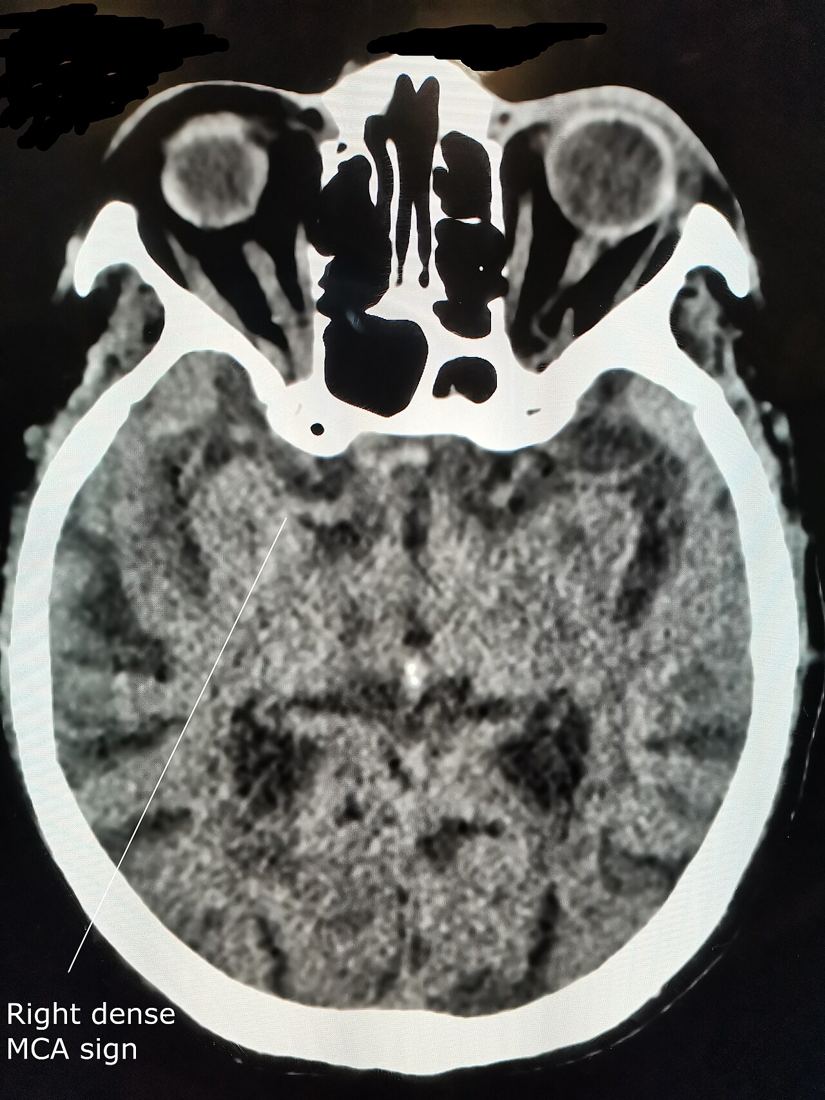
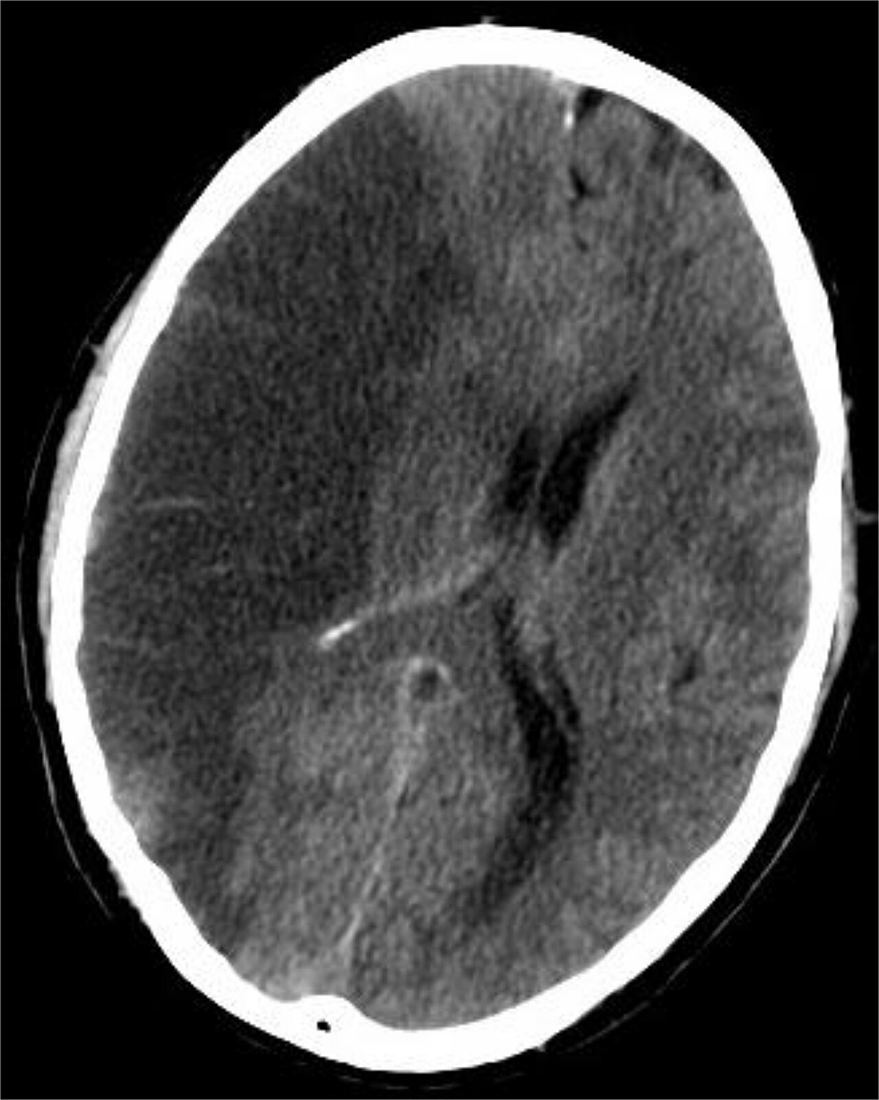
- Non-contrast CT or MRI, ideally within 25 minutes of arrival (Class 1).2,7
- CT angiography (with or without perfusion) if large-vessel occlusion is possible. Don't wait for creatinine (Class 1).2 Without perfusion imaging, use ASPECTS on CT to select for thrombectomy.7
- Thrombolyse without waiting for extra imaging that won't change the decision.2,5
- Give oxygen only if hypoxic, and treat fever.2
- Without recent anticoagulant or heparin use, don't wait for coagulation results to start the thrombolytic.3,4
Thrombolysis
| Drug | Adult dose | Notes |
|---|---|---|
| Tenecteplase | 0.25 mg/kg IV bolus over 5 s, max 25 mg. By weight: < 60 kg 15 mg · 60–69 kg 17.5 mg · 70–79 kg 20 mg · 80–89 kg 22.5 mg · ≥ 90 kg 25 mg | Single bolus. Half the STEMI dose: don't mix up the tables.2,3 |
| Alteplase | 0.9 mg/kg IV, max 90 mg: 10% as a bolus over 1 min, the rest over 60 min | Doses above 0.9 mg/kg may raise intracranial hemorrhage.4 |
Unreviewed doses. Verify against the current label and your institution's protocol before giving anything.
- Window: within 4.5 hours of onset or last known well (Class 1).2 The alteplase label still says within 3 hours. The 3–4.5 hour window rests on ECASS III.4,10
- Late or wake-up stroke: thrombolysis may be considered at 4.5–9 hours or with unknown onset when perfusion imaging or a DWI-FLAIR mismatch shows salvageable tissue.5 In WAKE-UP (n = 503), MRI-selected alteplase improved favorable outcome (53.3% vs 41.8%).11
- Monitor and control BP during and after the thrombolytic.3,4 In the NINDS trials, BP was kept at 185/110 mm Hg or lower for 24 hours.4
- Contraindications on the tenecteplase label (stroke): active intracranial hemorrhage, active internal bleeding, intracranial or spinal surgery or trauma within 2 months, known bleeding diathesis, severe uncontrolled hypertension, and intracranial neoplasm, AVM or aneurysm.3 The 2026 guideline also revised its approach to contraindications.1
What the trials show
- NINDS (0–3 h, alteplase): at least 30% more patients had minimal or no disability at 3 months. Symptomatic hemorrhage was 6.4% vs 0.6%, and mortality 17% vs 21% (not significant).12
- ECASS III (3–4.5 h): favorable outcome 52.4% vs 45.2%. Symptomatic hemorrhage 2.4% vs 0.2%.10
- AcT (tenecteplase vs alteplase, n = 1,600): modified Rankin 0–1 in 36.9% vs 34.8%, meeting noninferiority. Symptomatic hemorrhage was 3.4% vs 3.2%.13 Door-to-needle times were 36 vs 37 minutes.14
Guidelines treat thrombolysis as standard.1,2 Some emergency physicians remain skeptical. The SGEM review of AcT argues that the trial assumed alteplase works, that the NINDS and ECASS III results are contested, and that open-label design and telephone outcome scoring could favor the newer drug.15 REBEL EM also flags the open-label design, and notes that the evidence for thrombolytic efficacy itself remains debated.14
Minor, non-disabling stroke
- Thrombolysis is not recommended. Dual antiplatelet therapy is preferred.1,5
- PRISMS (NIHSS 0–5, not clearly disabling): alteplase did not beat aspirin (favorable outcome 78.2% vs 81.5%), and caused symptomatic hemorrhage in 3.2% vs 0%. The trial stopped early.16
- ARAMIS (n = 760): dual antiplatelet therapy was noninferior to alteplase (93.8% vs 91.4% excellent outcome). Symptomatic hemorrhage was 0.3% vs 0.9%.6
- POINT (minor stroke or high-risk TIA): clopidogrel plus aspirin lowered major ischemic events at 90 days (5.0% vs 6.5%), but raised major hemorrhage (0.9% vs 0.4%). Most events came in the first week.17
Thrombectomy
- Anterior proximal large-vessel occlusion: thrombectomy within 6 hours, and in selected patients at 6–24 hours on imaging and clinical criteria (Class 1, level A).2
- Large cores: now eligible in selected patients, including those with low ASPECTS.7,5
- Basilar occlusion: strong recommendation for thrombectomy up to 24 hours.5
- Older or mildly disabled patients: the 80-year age limit in the early window is gone, and thrombectomy is reasonable in selected patients with a prestroke modified Rankin of 2.5
- Medium or distal vessel occlusions: not routinely recommended outside trials.7
What the trials show
- HERMES (5 trials, n = 1,287): thrombectomy reduced 90-day disability (common OR 2.49). The number needed to treat for one patient to improve by at least one Rankin level was 2.6. Benefit held at age 80 and older.18
- DAWN (6–24 h, clinical-core mismatch): functional independence 49% vs 13%.19
- SELECT2 (large core, ASPECTS 3–5 or core ≥ 50 mL): functional independence 20% vs 7%, with more vascular complications.20
- ATTENTION (basilar, within 12 h): good outcome 46% vs 23%, and mortality 37% vs 55%.21
BP, glucose and early care
| Issue | 2026 guideline | Class |
|---|---|---|
| SBP < 140 after thrombolysis | No benefit from intensive lowering | 3: No benefit |
| SBP < 140 after successful thrombectomy | Harmful | 3: Harm |
| Intensive glucose lowering (80–130 mg/dL) | No benefit | 3: No benefit |
| Fever | Keep normothermic; treat hyperthermia | 1 |
| Oxygen | Only if hypoxic | 1 |
| Swallowing | Bedside dysphagia screen before anything by mouth | 1 |
| DVT prevention | Intermittent pneumatic compression if immobile | 1 |
| Antiplatelet | Early antiplatelet therapy | 1 |
| Where to admit | Organized stroke unit | 1 |
Classes as reported in a published summary of the guideline.2 Intensive glucose control means 80–130 mg/dL (4.4–7.2 mmol/L).5,22
Pitfalls
- Deciding on thrombolysis by NIHSS number alone. Ask whether the deficit is disabling.5
- Thrombolysing a minor, non-disabling deficit.1,16
- Using the STEMI tenecteplase table (up to 50 mg) for stroke (max 25 mg).3
- Waiting for creatinine before CT angiography.2
- Holding thrombectomy to see whether the thrombolytic works.7
- Pushing systolic BP below 140 after reperfusion.2,23
How strong is the evidence?
Thrombectomy for anterior large-vessel occlusion has strong, consistent randomized evidence.18,2 Thrombolysis within 4.5 hours is a Class 1 recommendation, but its trials remain debated in emergency medicine.2,15 Large-core and basilar trials are newer, and SELECT2 stopped early for efficacy.20,21 The guideline's full text was not accessible for this page, so recommendations come from the AHA release and two published summaries.7,2,5
On-shift teaching
Questions to ask a learner at the bedside. Tap a question to see the answer. Every answer uses facts cited above.
Q1What is the stroke dose of tenecteplase, and how does it differ from STEMI?
Q2A patient has an NIHSS of 2 from mild hand clumsiness that doesn't affect function. Thrombolyse?
Q3Why not wait for a creatinine before the CT angiogram?
Q4A patient woke up with a stroke. Is thrombolysis off the table?
Q5After a successful thrombectomy, should you target systolic BP under 140?
References
What this page is built on
23 sources, cited 95 times. Dots are sources, filled by how far each was read; stronger color means a larger share of the citations. Tap a tier to see its sources.
Checked by the writer, not a physician. The dots show how each source was read, not that anyone has confirmed the claims.
- 1Prabhakaran S, Gonzalez NR, Zachrison KS, et al. 2026 Guideline for the Early Management of Patients With Acute Ischemic Stroke: a guideline from the American Heart Association/American Stroke Association. Stroke. 2026;57(8):e316–e436.
- 2Boettger P, Agarwal A, Omar OA, et al. A global health perspective on the 2026 AHA/ASA stroke guidelines: lessons from the Indian health system. Cerebrovasc Dis. 2026. (States guideline recommendations with class and level of evidence.)
- 3TNKase (tenecteplase) for injection. Genentech. FDA prescribing information, DailyMed.
- 4Activase (alteplase) for injection. Genentech. FDA prescribing information, DailyMed.
- 5Aykaç Ö, Şengeze N. 2026 AHA/ASA guideline for the early management of acute ischemic stroke: updates with implications for clinical practice. Turk J Cerebrovasc Dis. 2026;32(1):59–62.
- 6Chen HS, Cui Y, Zhou ZH, et al. Dual antiplatelet therapy vs alteplase for patients with minor nondisabling acute ischemic stroke: the ARAMIS randomized clinical trial. JAMA. 2023;329(24):2135–2144.
- 7American Heart Association Newsroom. New guideline expands stroke treatment for adults, offers first pediatric stroke guidance. January 26, 2026.
- 8Grotta JC, Yamal JM, Parker SA, et al. Prospective, multicenter, controlled trial of mobile stroke units (BEST-MSU). N Engl J Med. 2021;385(11):971–981.
- 9Pérez de la Ossa N, Abilleira S, Jovin TG, et al. Effect of direct transportation to thrombectomy-capable center vs local stroke center on neurological outcomes in patients with suspected large-vessel occlusion stroke in nonurban areas: the RACECAT randomized clinical trial. JAMA. 2022;327(18):1782–1794.
- 10Hacke W, Kaste M, Bluhmki E, et al. Thrombolysis with alteplase 3 to 4.5 hours after acute ischemic stroke (ECASS III). N Engl J Med. 2008;359(13):1317–1329.
- 11Thomalla G, Simonsen CZ, Boutitie F, et al. MRI-guided thrombolysis for stroke with unknown time of onset (WAKE-UP). N Engl J Med. 2018;379(7):611–622.
- 12National Institute of Neurological Disorders and Stroke rt-PA Stroke Study Group. Tissue plasminogen activator for acute ischemic stroke. N Engl J Med. 1995;333(24):1581–1587.
- 13Menon BK, Buck BH, Singh N, et al. Intravenous tenecteplase compared with alteplase for acute ischaemic stroke in Canada (AcT). Lancet. 2022;400(10347):161–169.
- 14Durrani M. The AcT trial: tenecteplase vs alteplase for acute ischemic stroke. REBEL EM; February 1, 2024.
- 15Milne K, with guest skeptic Fatovich D. You don't have to AcT that way: TNK for acute ischemic stroke. The Skeptics' Guide to Emergency Medicine; September 2022.
- 16Khatri P, Kleindorfer DO, Devlin T, et al. Effect of alteplase vs aspirin on functional outcome for patients with acute ischemic stroke and minor nondisabling neurologic deficits: the PRISMS randomized clinical trial. JAMA. 2018;320(2):156–166.
- 17Johnston SC, Easton JD, Farrant M, et al. Clopidogrel and aspirin in acute ischemic stroke and high-risk TIA (POINT). N Engl J Med. 2018;379(3):215–225.
- 18Goyal M, Menon BK, van Zwam WH, et al. Endovascular thrombectomy after large-vessel ischaemic stroke: a meta-analysis of individual patient data from five randomised trials (HERMES). Lancet. 2016;387(10029):1723–1731.
- 19Nogueira RG, Jadhav AP, Haussen DC, et al. Thrombectomy 6 to 24 hours after stroke with a mismatch between deficit and infarct (DAWN). N Engl J Med. 2018;378(1):11–21.
- 20Sarraj A, Hassan AE, Abraham MG, et al. Trial of endovascular thrombectomy for large ischemic strokes (SELECT2). N Engl J Med. 2023;388(14):1259–1271.
- 21Tao C, Nogueira RG, Zhu Y, et al. Trial of endovascular treatment of acute basilar-artery occlusion (ATTENTION). N Engl J Med. 2022;387(15):1361–1372.
- 22Johnston KC, Bruno A, Pauls Q, et al. Intensive vs standard treatment of hyperglycemia and functional outcome in patients with acute ischemic stroke: the SHINE randomized clinical trial. JAMA. 2019;322(4):326–335.
- 23Ghozy S, Mortezaei A, Elfil M, et al. Intensive vs conventional blood pressure control after thrombectomy in acute ischemic stroke: a systematic review and meta-analysis. JAMA Netw Open. 2024;7(2):e240179.
AI-generated draft. Not reviewed by a physician. This page is for education only and may contain errors, including in doses. Do not use it to diagnose, treat or make decisions about any patient. Rely on your own clinical judgment, your institution's protocols and current drug labeling. Reading this page does not create a physician-patient relationship. Full terms